

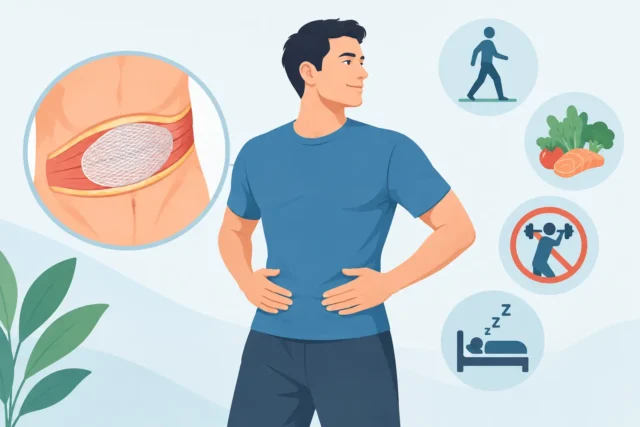
 I see incisional hernias return often. They can return months or years after abdominal surgery, even after you feel normal again.
I write this to help prevent a recurrence.
My goal is not just to close a hole. I assess the anatomy. I choose the right technique. I support healing long after surgery.
Why Incisional Hernias Recur
An incisional hernia develops when tissue pushes through a weakness at the site of a previous abdominal incision. The original operation may have been performed for a cesarean delivery, bowel surgery, gallbladder surgery, cancer treatment, emergency abdominal surgery, or another condition. Some hernias appear soon after recovery, while others develop gradually over several years.
Recurrence does not automatically mean that a previous operation was performed poorly. Hernia repair is influenced by factors that can be difficult to control, including the size and location of the defect, the quality of the abdominal wall tissue, prior infection, and the need for emergency surgery.
A large midline hernia after multiple abdominal procedures carries a different level of complexity as compared to a small defect after a single laparoscopic port-site incision.
Several factors can raise the likelihood of recurrence:
- Excess abdominal pressure from obesity, chronic coughing, constipation, or heavy lifting
- Smoking or nicotine exposure, which reduces blood flow and impairs tissue healing
- Diabetes that is not well controlled
- Wound infection or fluid collection after surgery
- Poor nutrition, anemia, or low protein levels
- Steroid use, immune-suppressing medicines, and certain connective-tissue disorders
In my vast practice of 30+ yrs ,I have seen that one risk factor does not determine the outcome.So the repair strategy and recovery plan should be individualized.
Prevent Incisional Hernia Recurrence Before Surgery
The most effective prevention often begins before the operating room. A recurrent hernia repair should not be treated as a routine repeat procedure. Surgeon needs to understand the previous operation, the type and position of any existing mesh, the dimensions of the hernia, and whether bowel is involved in the defect.
Obtain detailed imaging and surgical planning
I use CT scan of the abdomen to map the hernia and assess the abdominal wall. It can show the width of the defect, the condition of the muscles, the position of prior mesh, and whether there are multiple weak areas.
This information helps determine whether a minimally invasive laparoscopic or robotic approach is appropriate, or whether an open abdominal wall reconstruction is safer.
The best technique depends on the individual case. Laparoscopic and robotic approaches can reduce the size of incisions and may support a more comfortable early recovery in selected patients.
However, very large, complex, infected, or multiply recurrent hernias may require an open approach to restore the abdominal wall properly. The priority is a durable, safe repair rather than using one technique for every patient.
Address modifiable risk factors
When surgery is elective, taking time to improve health beforehand can materially improve healing. Weight reduction may lower tension on the repair and reduce pressure inside the abdomen.
For patients with severe obesity,must loose weight first.The timing of bariatric treatment and hernia repair should be discussed carefully, since the right sequence depends on symptoms, hernia size, and overall health.
Smoking cessation is one of the most meaningful step, I advise patient . Nicotine in cigarettes, vaping products, and other sources can impair wound healing.
Diabetes should be controlled as well as possible before surgery, and chronic lung conditions should be reviewed if coughing is frequent. Treating constipation is also practical: repeated straining can place considerable pressure on a healing abdominal wall.
Nutrition deserves equal attention. Patients who have lost weight unintentionally, have undergone previous bowel surgery, or have chronic illness may need assessment for low protein levels, vitamin deficiencies, or anemia. A repair is stronger when the body has the resources to heal.
The Surgical Choices That Support a Durable Repair
Mesh is commonly used in incisional hernia repair because it reinforces the abdominal wall and can reduce recurrence compared with suture-only repair in many cases.
Yet mesh is not a single product or a universal solution. The material, size, placement plane, fixation method, and relationship to the bowel must all be selected according to the hernia and the patient.
Whenever feasible, surgeons aim to restore the abdominal wall anatomy rather than merely bridge a gap. Closing the fascial defect and placing mesh in a well-vascularized tissue plane can distribute tension more effectively.
Complex abdominal wall reconstruction may involve techniques that release or reposition muscle layers to achieve closure without excessive tension. These decisions require experience in advanced hernia and gastrointestinal surgery.
Previous mesh does not always need to be removed. Removal can increase the risk of injury to bowel, bleeding, and infection when mesh is well incorporated and not causing a problem.
On the other hand, infected, exposed, migrated, painful, or poorly positioned mesh may need to be addressed. This is why revision surgery should be planned after reviewing prior operative records and imaging whenever available.
Preventing surgical-site infection is another essential part of recurrence prevention. Meticulous tissue handling, appropriate antibiotic use, blood sugar control, and management of fluid collections all matter. In selected high-risk cases, we recommend additional measures based on the condition of the wound and abdominal wall.
Recovery Habits That Protect the Repair
The repair remains biologically vulnerable during the early healing period, even when pain is improving. Patients should follow the activity instructions provided by our surgical team rather than relying on a fixed timeline found online.
Restrictions vary according to the size of the hernia, the method of repair, whether abdominal wall reconstruction was required, and the physical demands of the patient’s work.
We encourage Walking early because it supports circulation, lung function, bowel movement, and recovery. Heavy lifting, strenuous core exercises, and sudden twisting should be reintroduced gradually.
A patient whose work involves lifting, driving long distances, or physical labor may require a more structured return-to-work plan than someone with a desk-based role.
Pain control matters because severe pain can lead to shallow breathing, immobility, and difficulty coughing safely. At the same time, persistent or increasing pain should not be dismissed.
Fever, wound redness, drainage, vomiting, inability to pass stool or gas, rapidly increasing swelling, or a painful irreducible bulge require prompt medical assessment.
We advise to avoiding constipation,it is simple but important part of recovery. Adequate fluids, dietary fiber when appropriate, gentle walking, and prescribed stool softeners can reduce straining.
Patients with chronic cough, prostate-related urinary straining, or ongoing bowel symptoms must discuss these conditions with the surgeon, since untreated pressure can challenge the repair over time.
Follow-Up Is Part of Hernia Treatment
A successful operation is not the final step in care. Follow-up visits allow the us to monitor wound healing, assess pain, guide activity progression, and identify problems such as seroma formation or infection early.
Not every postoperative bulge represents a recurrent hernia. Fluid under the skin, swelling, and normal tissue healing can create a temporary fullness, but it should be assessed rather than assumed to be harmless.
Long-term weight management, smoking avoidance, diabetes care, and treatment of chronic constipation or cough remain relevant after the incision has healed. These measures protect both the repair and broader digestive and metabolic health.
For complex or recurrent cases, seeking an opinion from a surgeon experienced in minimally invasive, robotic, and abdominal wall reconstruction techniques can help patients understand the options without rushing into another operation.
I ,Dr. Arindam Ghosh provide individualized evaluation for hernia patients through leading hospital facilities in Dubai and Sharjah, with treatment planning based on anatomy, prior surgery, and personal recovery goals.
If you notice a new bulge, discomfort with activity, or symptoms after a previous repair, arrange for a specialist consult.This information is educational and does not replace an in-person consultation. If you have concerning symptoms, please see your surgical team promptly.